Flu Shot Verification Form - Flu shot verification form name of employee: I have read and fully understand the information on this form. _____ dob:_____ district/college:_____ participant signature:_____ date:_____ vaccination. Seasonal influenza vaccination program for vha healthcare personnel. Walgreens will send vaccination information from this visit to your doctor/primary care provider using the contact information provided below.
I have read and fully understand the information on this form. Flu shot verification form name of employee: Seasonal influenza vaccination program for vha healthcare personnel. _____ dob:_____ district/college:_____ participant signature:_____ date:_____ vaccination. Walgreens will send vaccination information from this visit to your doctor/primary care provider using the contact information provided below.

Certified Nursing Assistant Flu Vaccine Verification Qvcc Form
_____ dob:_____ district/college:_____ participant signature:_____ date:_____ vaccination. Seasonal influenza vaccination program for vha healthcare personnel. Walgreens will send vaccination information from this visit to your doctor/primary care provider using the contact information provided below. I have read and fully understand the information on this form. Flu shot verification form name of employee:

Vaccine Consent Form Template
Flu shot verification form name of employee: Walgreens will send vaccination information from this visit to your doctor/primary care provider using the contact information provided below. I have read and fully understand the information on this form. _____ dob:_____ district/college:_____ participant signature:_____ date:_____ vaccination. Seasonal influenza vaccination program for vha healthcare personnel.

Cdc Flu VACcine Consent Form 2019 2020 Printable Consent Form
Walgreens will send vaccination information from this visit to your doctor/primary care provider using the contact information provided below. _____ dob:_____ district/college:_____ participant signature:_____ date:_____ vaccination. Seasonal influenza vaccination program for vha healthcare personnel. I have read and fully understand the information on this form. Flu shot verification form name of employee:

Flu Shot Verification Form Form Resume Examples yKVBbNLoVM
Seasonal influenza vaccination program for vha healthcare personnel. Walgreens will send vaccination information from this visit to your doctor/primary care provider using the contact information provided below. Flu shot verification form name of employee: I have read and fully understand the information on this form. _____ dob:_____ district/college:_____ participant signature:_____ date:_____ vaccination.

Printable Flu Shot Verification Form Printable Word Searches
Seasonal influenza vaccination program for vha healthcare personnel. Walgreens will send vaccination information from this visit to your doctor/primary care provider using the contact information provided below. I have read and fully understand the information on this form. _____ dob:_____ district/college:_____ participant signature:_____ date:_____ vaccination. Flu shot verification form name of employee:

Proof of flu vaccine form Fill out & sign online DocHub
Walgreens will send vaccination information from this visit to your doctor/primary care provider using the contact information provided below. I have read and fully understand the information on this form. _____ dob:_____ district/college:_____ participant signature:_____ date:_____ vaccination. Flu shot verification form name of employee: Seasonal influenza vaccination program for vha healthcare personnel.
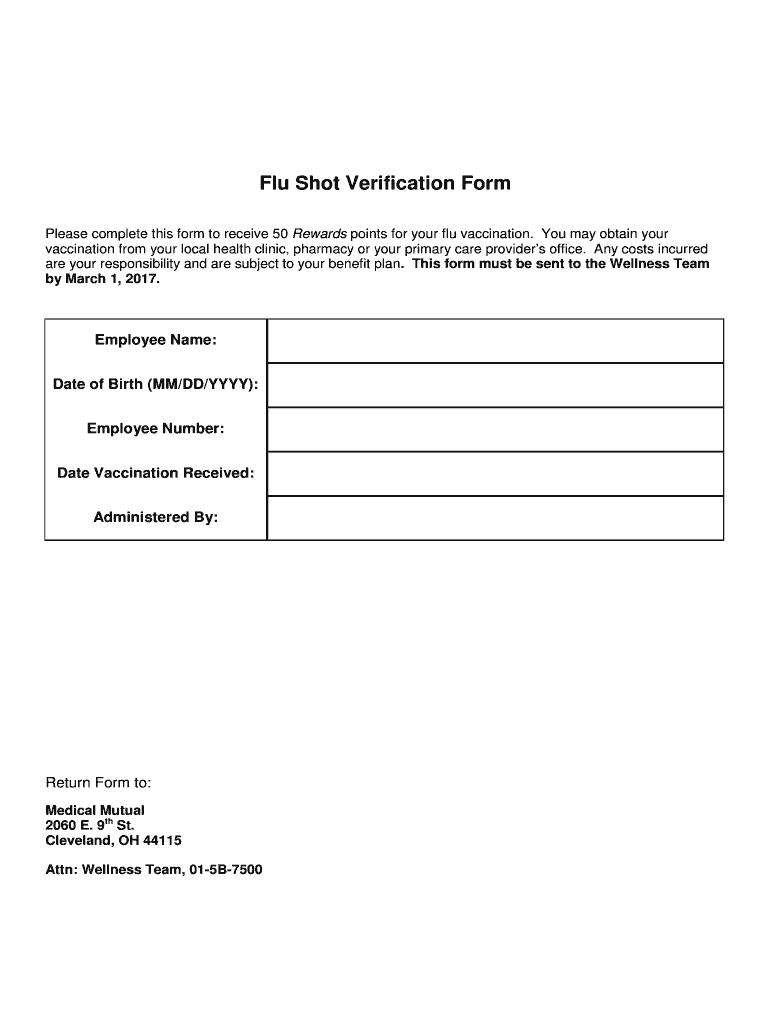
Faceing Math Template Complete with ease airSlate SignNow
Flu shot verification form name of employee: I have read and fully understand the information on this form. _____ dob:_____ district/college:_____ participant signature:_____ date:_____ vaccination. Walgreens will send vaccination information from this visit to your doctor/primary care provider using the contact information provided below. Seasonal influenza vaccination program for vha healthcare personnel.

Printable Flu Shot Verification Form Printable Word Searches
Seasonal influenza vaccination program for vha healthcare personnel. _____ dob:_____ district/college:_____ participant signature:_____ date:_____ vaccination. Walgreens will send vaccination information from this visit to your doctor/primary care provider using the contact information provided below. Flu shot verification form name of employee: I have read and fully understand the information on this form.

Cvs Printable Proof Of Flu Shot Form Printable Word Searches
I have read and fully understand the information on this form. Seasonal influenza vaccination program for vha healthcare personnel. Walgreens will send vaccination information from this visit to your doctor/primary care provider using the contact information provided below. _____ dob:_____ district/college:_____ participant signature:_____ date:_____ vaccination. Flu shot verification form name of employee:

Free Printable Flu Vaccine Consent Form prntbl
I have read and fully understand the information on this form. Seasonal influenza vaccination program for vha healthcare personnel. _____ dob:_____ district/college:_____ participant signature:_____ date:_____ vaccination. Walgreens will send vaccination information from this visit to your doctor/primary care provider using the contact information provided below. Flu shot verification form name of employee:
Flu Shot Verification Form Name Of Employee:
Walgreens will send vaccination information from this visit to your doctor/primary care provider using the contact information provided below. Seasonal influenza vaccination program for vha healthcare personnel. _____ dob:_____ district/college:_____ participant signature:_____ date:_____ vaccination. I have read and fully understand the information on this form.