Patient Responsibility For Non Covered Services Form - Service(s) not paid for by the benefit plan (practice name) accepts (plan. I request that payment of authorized medicare and/or medicaid benefits to me or on my behalf.
Service(s) not paid for by the benefit plan (practice name) accepts (plan. I request that payment of authorized medicare and/or medicaid benefits to me or on my behalf.

Nursing Home Patient Financial Responsibility Form Template Edit
I request that payment of authorized medicare and/or medicaid benefits to me or on my behalf. Service(s) not paid for by the benefit plan (practice name) accepts (plan.

Top 8 Patient Financial Responsibility Form Templates free to download
Service(s) not paid for by the benefit plan (practice name) accepts (plan. I request that payment of authorized medicare and/or medicaid benefits to me or on my behalf.

Patient Financial Responsibility Agreement Template PDF Template
Service(s) not paid for by the benefit plan (practice name) accepts (plan. I request that payment of authorized medicare and/or medicaid benefits to me or on my behalf.
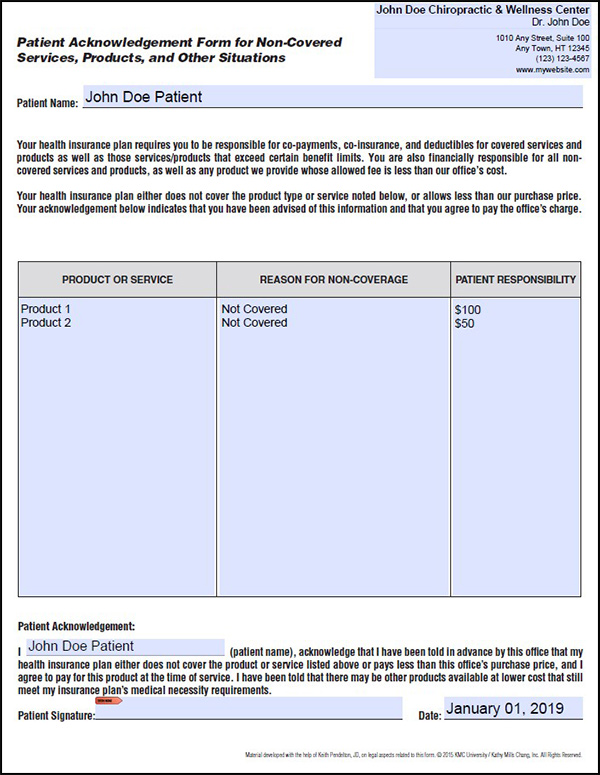
Patient Acknowledgement Form for NonCovered Services KMC University
I request that payment of authorized medicare and/or medicaid benefits to me or on my behalf. Service(s) not paid for by the benefit plan (practice name) accepts (plan.

Fillable Online Patient Billing Acknowledgement Form NonCovered
Service(s) not paid for by the benefit plan (practice name) accepts (plan. I request that payment of authorized medicare and/or medicaid benefits to me or on my behalf.
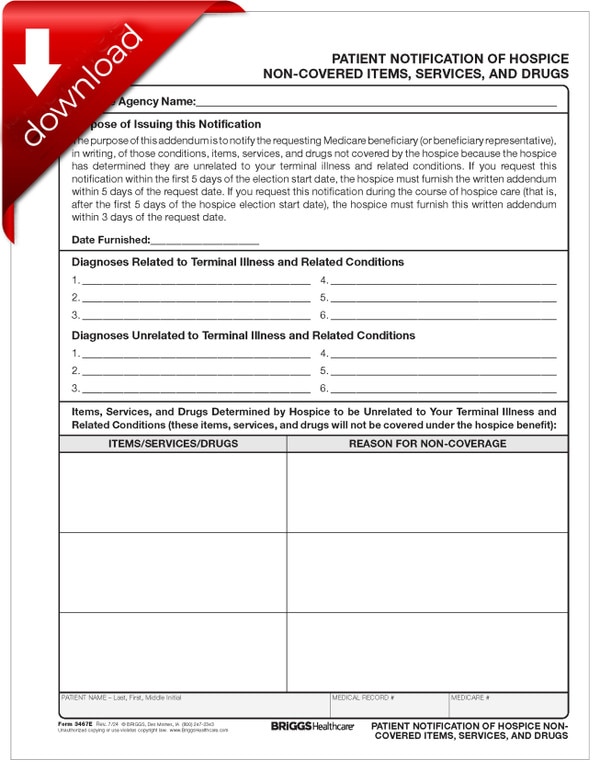
Patient Notification of Hospice NonCovered Items, Services, & Drugs
Service(s) not paid for by the benefit plan (practice name) accepts (plan. I request that payment of authorized medicare and/or medicaid benefits to me or on my behalf.

Medicaid Provider Agreement Non Institutional 20122025 Form Fill Out
I request that payment of authorized medicare and/or medicaid benefits to me or on my behalf. Service(s) not paid for by the benefit plan (practice name) accepts (plan.

Fillable Online NONCOVERED SERVICES AGREEMENT Fax Email Print pdfFiller
Service(s) not paid for by the benefit plan (practice name) accepts (plan. I request that payment of authorized medicare and/or medicaid benefits to me or on my behalf.
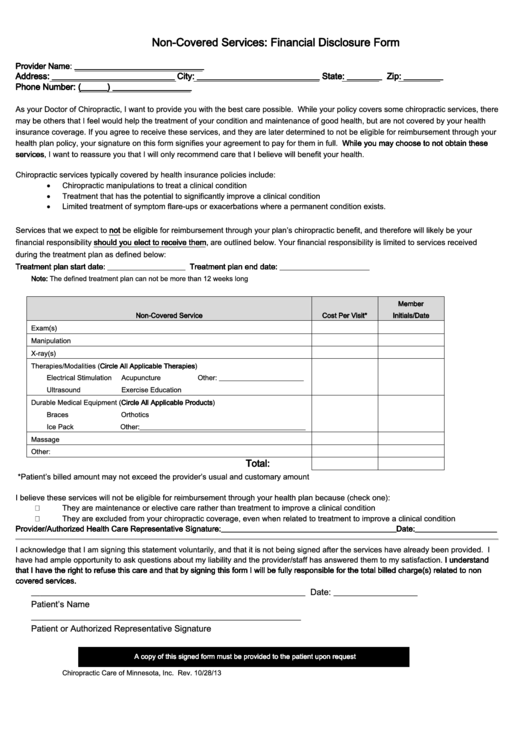
NonCovered Services Financial Disclosure Form 2013 printable pdf download
I request that payment of authorized medicare and/or medicaid benefits to me or on my behalf. Service(s) not paid for by the benefit plan (practice name) accepts (plan.

Trocar Non Covered Services Waiver Form Fill Out and Sign Printable
Service(s) not paid for by the benefit plan (practice name) accepts (plan. I request that payment of authorized medicare and/or medicaid benefits to me or on my behalf.
Service(S) Not Paid For By The Benefit Plan (Practice Name) Accepts (Plan.
I request that payment of authorized medicare and/or medicaid benefits to me or on my behalf.